The Department of Health Services (DoHS), Ministry of Health and Population has released a guideline Warehouse Management Guideline (Booklet). This guideline has prepared under the leadership of Management Division, DoHS to provide a technical guidance on Warehouse management in different level of stores in Nepal.

Guideline on Safely Dispose of Unused or Expired Medicine, Chemicals and Medicine related Commodities 2078
The Department of Health Services (DoHS), Ministry of Health and Population has released a new guideline on Safely Dispose of Unused or Expired Medicine, Chemicals and Medicine related Commodities 2078. This guideline has prepared under the leadership of Environment Health and Health Care Waste Management Section, Management Division.
Public health milestones through the years
Since the foundation of the World Health Organization in 1948, the world has experienced public health challenges that have required us all to come together with science, solutions and solidarity. This timeline, published in 2023 on the occasion of WHO’s 75th anniversary, serves as a reminder of some of the most memorable successes and how these have contributed to improved health across the world. These milestone achievements also provide inspiration for us to face the health challenges of the future.
- 1945: Planning for WHO
- 1946: WHO Constitution approved
- 1947: First-ever global disease-tracking service
- 1950: Discovery of antibiotics
- 1952: Inactivated polio vaccine: Jonas Salk develops the inactivated poliovirus vaccine (given by injection), paving the way for mass global campaigns facilitated by countries, WHO and other partners that have led to the near-eradication of polio.
- 1961: Attenuated live-virus polio vaccine: Albert Sabin develops the attenuated live-virus vaccine (given orally), paving the way for mass global campaigns facilitated by countries, WHO and other partners that have led to the near-eradication of polio.
- 1969: International Health Regulations: The World Health Assembly establishes the first International Health Regulations, which represent an agreement between WHO Member States to work together to prevent and respond to acute public health risks that have the potential to cross borders and threaten people worldwide.
- 1972: Special Programme of Research, Development and Research Training in Human Reproduction: The Special Programme of Research, Development and Research Training in Human Reproduction (HRP) is created at WHO. It is the sole body within the UN system with a global mandate to carry out research into sexual and reproductive health and rights.
- 1974: Expanded Programme on Immunization: WHO founds the Expanded Programme on Immunization to bring life-saving vaccines to all the world’s children.
- 1975: Special Programme for Research and Training in Tropical Diseases
- 1977: First Essential Medicines List
- 1978: “Health for All” goal set: The International Conference on Primary Health Care, in Alma-Ata, Kazakhstan, sets the aspirational goal, “Health for All”, laying the groundwork for WHO’s call for universal health coverage.
- 1978: Global diarrhoeal diseases programme
- 1980: Smallpox eradication: Following an ambitious 12-year global vaccination campaign led by WHO, smallpox is eradicated.
- 1981: International Code of Marketing Breastmilk Substitutes
- 1983: HIV discovered: The Human immunodeficiency virus (HIV), which causes AIDS, is discovered. In 1987, the first antiretroviral medication to control HIV infection and prevent it from progressing to AIDS is licensed, prompting a shift in WHOs priorities.
- 1988: Global Polio Eradication Initiative
- 1994: Comprehensive definition of reproductive health
- 1995: Integrated Management of Childhood Illness (IMCI) strategy
- 1998: Emergency contraception
- 1999: Global Alliance for Vaccines and Immunization
- 1999: Global strategy for noncommunicable diseases
- 2000: Millennium Development Goals
- 2000: GOARN: The WHO Global Outbreak Alert and Response Network (GOARN) is established to detect and combat the international spread of outbreaks.
- 2001: UN Declaration of Commitment on HIV/AIDS
- 2001: Global Fund: The Global Fund to fight AIDS, Tuberculosis and Malaria, a new partnership and funding mechanism initially hosted by WHO, is created in collaboration with other UN agencies and major donors.
- 2003: “3 by 5” initiative: WHO launches the “3 by 5” initiative, which aims to bring treatment to 3 million people living with HIV by 2005 and lays the groundwork for reaching 13 million people infected with HIV with antiretroviral treatment by 2013.
- 2003: Framework Convention on Tobacco Control: The World Health Assembly unanimously adopts WHO’s first global public health treaty, the WHO Framework Convention on Tobacco Control, which aims to reduce tobacco-related deaths and disease worldwide.
- 2004: UN Road Safety Collaboration: The UN Road Safety Collaboration is established. WHO and the World Bank launch the first ever world report on road traffic injury prevention.
- 2004: New Strategic Operations Centre for emergency response
- 2005: International Health Regulations revised
- 2006: Child mortality declines: The number of children who die before their fifth birthday declines below 10 million for the first time in recent history.
- 2006: Child Growth Standards: WHO Child Growth Standards are launched to help every child grow in an equitable way.
- 2008: Heart disease and stroke: Heart disease and stroke emerge as the world’s number one killers ̶ indicating a global shift from infectious diseases to noncommunicable diseases, noted the World Health Statistics report.
- 2009: New H1N1 virus: The world braces itself for the first influenza pandemic since 1968 with the emergence of the new H1N1 influenza virus.
- 2010: Options for raising resources for health: WHO issues a menu of options for raising sufficient resources and removing financial barriers so that all people, especially those with limited resources to spend on health care, have access to essential health services.
- 2010: First rapid molecular test for detection of TB
- 2011: Pandemic Influenza Preparedness Framework
- 2012: NCD targets: For the first time, WHO Member States set global targets to prevent and control heart disease, diabetes, cancer, chronic lung disease and other diseases.
- 2012: Nutrition plan: The World Health Assembly adopts WHO’s implementation plan on maternal, infant, and young child nutrition.
- 2013: Comprehensive Mental Health Action Plan: The first global Comprehensive Mental Health Action Plan is endorsed. More than 100 countries have used the Mental Health GAP Action Programme (mhGAP) for the integration of mental health at primary health care level since that time.
- 2014: Every Newborn Action Plan: The Every Newborn Action Plan is endorsed by the World Health Assembly. The Plan presents evidence-based solutions to prevent newborn deaths and stillbirths. It sets out a clear path with specific global and national milestones to achieve the SDG target of at least as low as 12 newborn deaths or less per 1000 live births.
- 2014: Ebola outbreak in West Africa
- 2015: HIV treatment coverage
- 2015: Elimination of mother-to-child transmission of HIV and syphilis
- 2015: Interruption of indigenous malaria transmission
- 2015: Child-friendly formulations of anti-TB medicines
- 2015: Sustainable Development Goals
- 2016: UN Declaration on antimicrobial resistance
- 2016: Progress towards polio-free certification in African Region
- 2016: Treatment of neglected tropical diseases
- 2016: Global Strategy for Women’s, Children’s and Adolescents’ Health
- 2016: Ebola outbreak in West Africa: progress
- 2016: Zika association declared a Public Health Emergency of International Concern
- 2017: Antibiotic-resistant “priority pathogens”: WHO publishes its first ever list of antibiotic-resistant “priority pathogens” – a catalogue of 12 families of bacteria that pose the greatest threat to human health.
- 2017: Partnership for Healthy Cities
- 2019: UN Declaration on universal health coverage
- 2020: Global outbreak of novel coronavirus declared a Public Health Emergency of International Concern
- 2020: New SDG indicator on blood stream infections
- 2020: First oral regimen for treatment of multidrug-resistant tuberculosis
- 2020: Access to COVID-19 Tools Accelerator
- 2021: Antiretroviral therapy
- 2021: Malaria vaccine for children
- 2021: Tuberculosis prevention and care
- 2022: Agreement for cooperation on the health of humans, animals, plants and the environment
- 2022: Updated edition of “Family Planning: A Global Handbook for Providers”
- 2023: Looking back – and forwards.
Source of Info: WHO
A critical lesson from the COVID-19 pandemic is that we must invest in strengthening the health workforce to enable equitable pandemic prevention, preparedness, and response and deliver essential health services. The following are urgent actions that finance ministers, health ministers, other policymakers, and donors must undertake at all levels to prepare the workforce for the future and ensure universal health coverage.
- Allocate increased, dedicated funding for long-term health systems and health workforce strengthening. Donors should support low- and middle-income countries’ health system reforms to build and sustain their health workforce, including nurses, midwives, and community health workers (CHWs). National-level stakeholders, including ministries of health, ministries of finance, and the private sector should collaborate to expand fiscal space and align budgeting for the health workforce needed for universal health coverage.
- Train and employ new health workers and retain existing health workers to meet health needs. Provide fair and timely pay and career advancement opportunities. Ensure gender equitable preservice training, recruitment, and compensation. Provide supportive supervision, continuing in-service education, and supplies and commodities to enable health workers to deliver high-quality and responsive health services and improve population health outcomes. Define workforce standards with a gender lens and include responsibilities and tasks, educational guidelines, and minimum competency requirements.
- Ensure safe and decent work for all health workers, including women and community health workers. Provide health workers adequate protection, including personal protective equipment, and ensure adequate water, sanitation, and hygiene services. Address violence against health workers and foster policies and investments that improve their working conditions, including by preventing and addressing gender-based exploitation, abuse, and harassment. Ensure adequate infrastructure and access to health services for all health workers—including mental health care and vaccination—without financial hardship.
- Integrate community health workers into national health systems and pay them fairly. CHWs in particular are under-supported, even though they play a crucial role in pandemic response and providing quality care, and they could be tapped to do even more. Many CHWs are not paid or are underpaid, and most of them are women. Collect data on all health workers disaggregated by gender, age, type, location, and contract; track service delivery and health outcome information; and use data for better informed workforce planning. Services provided by community health workers, in particular, must be tracked separately to optimize resources and impact.
- Involve frontline health workers—including women, nurses, midwives, and community health workers—in health policymaking, including emergency response committees, budget planning, and donor consultations so that their needs and lived realities are considered. Ensure global health initiatives include frontline health workers in health policy planning bodies, such as in Global Fund Country Coordinating Mechanisms and ensure frontline health workers are included in key planning processes, such as the development of PEPFAR Country Operational Plans and proposals to the Pandemic Fund.
Source of Info: Top Policy Recommendations to Invest in Health Workers.
Oxfam Young Leaders Fellowship Programme 2023
- Are you a feminist activist challenging patriarchy and social norms and have innovative ideas for gender justice?
- Are you an artist, writer/story teller or photo journalist or videographer capturing and disseminating peoples stories for freedom and social justice?
- Are you a freelance journalist, digital media activist/practitioner aspiring to promote democratic values and civic space, ensuring data justice and digital rights?
- Are you a technology enthusiast and aspiring to ensure that digital technologies advance gender equality, social justice and civic space without compromising individual privacy and freedom?
- Are you a grassroots activist, community organizer believing in peoples power to bring social change?
- Are you leading small business leader or climate change activist trying to promote inclusive and responsible business and striving that both governments and business care for climate change?
Then this fellowship is designed for you!
Oxfam International will launch the fellowship for the first cohort of fellows this year with Asia Centre as the implementing partner. The fellowship will fund eight young people to work on an idea of their choice which could strengthen civic space in their country or address concerns of rising inequality, climate change, gender justice and social justice.
The programme will provide tools to empower young people with hands-on training and close mentorship to strengthen their capacity to make social change happen. Oxfam senior staff and its partners will mentor and provide guidance to the fellows to develop their leadership skills, help them execute their projects, and widen access to regional, local and global civil society and advocacy networks.
Benefits
- International learning opportunity and exposure
- Fixed fellowship amount to be paid quarterly basis and an annual fixed amount for project execution
- Opportunity to be mentored by experienced international professionals in various fields
- Opportunity to work with Oxfam Leadership and cohorts from different regions
- Support to independently organise smaller network for influencing and campaigning
- An opportunity to understand and learn about the United Nations, Multi-lateral institutions and international development sector
Eligibility
Prospective young fellows must meet the following criteria:
- Aged 27 or below
- Be a citizen of one of the following countries with an Oxfam office: Bangladesh, Cambodia, China, Hong Kong-SAR, India, Indonesia, Laos, Myanmar, Nepal, Pakistan, Philippines, Thailand, Timor-Leste, or Vietnam
- A postgraduate degree with exceptional leadership quality and talents
- Those with professional graduate degrees and experience of working with civic organization and civic spaces will also be considered
- Commitment to human rights, civic rights, and gender rights
- A keen interest to work on issues related economic inequality, climate justice, gender rights, data justice and digital rights, and strengthening civic rights and spaces
- Ability to design and implement a project independently
- Those with background in digital technology, management, media, and development are encouraged to apply
- Women and people from diverse backgrounds are encouraged to apply
Fellows Deliverables
- Propose, co-design, and complete a 9-month long project on a subject of their choice related to issues of civic activism, social justice, gender justice, climate justice or inequality
- Organize a network of at least 50 young people committed to civic space and rights in the chosen country – online and offline. Providing leadership training support to young people
- Dedicate a minimum of 40 hours per month towards implementing the proposed project for a period of 9 months
- Attend an in-person training workshop for 5 days in Bangkok
- Periodically report progress and challenges to mentors
- The fellows will be required to submit their work for external publication on the “Civic Asia” website and identify opportunities to populate the website
- Work closely with Oxfam in the hosting country
Language Proficiency
- English language competency is preferred for the fellows to be able to engage with all aspects of digital platforms and Oxfam resources. Competency in local languages will be an added advantage.
Application Process
- Candidates must submit their resume, letter of motivation, and a project pitch for the duration of the fellowship via this Google Form.
- Short-listed candidates will be interviewed by a panel of judges with the criteria (see Judging Criteria below) to select eight young fellows who will participate in the programme.
To apply for the fellowship, fill in this Google Form.
If you have any questions regarding the application process, please email: contact@asiacentre.org.
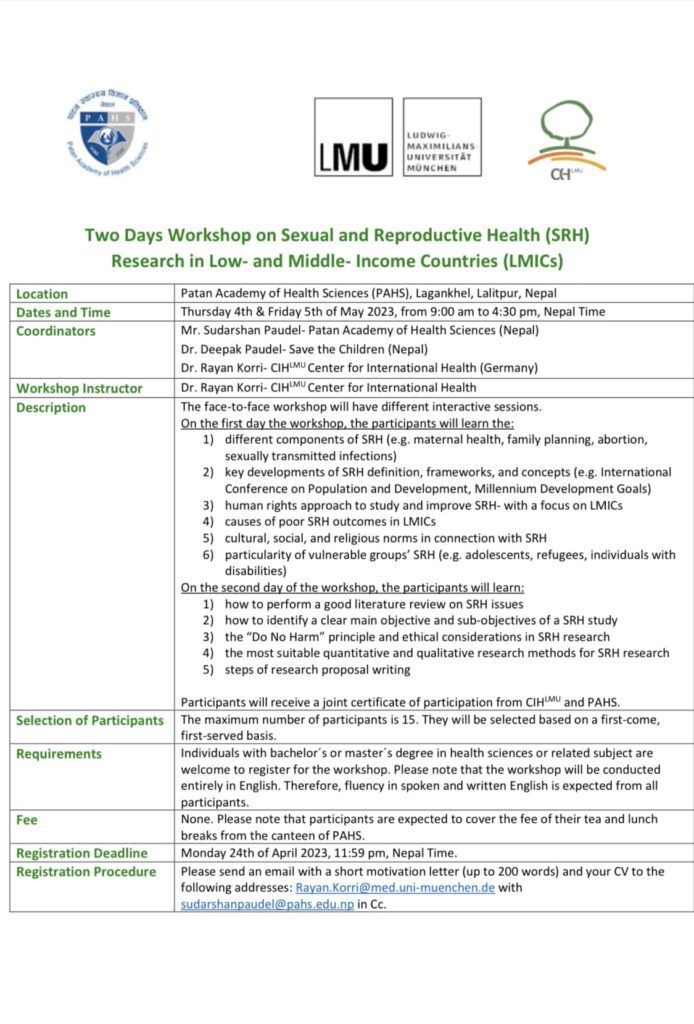
The Center for International Health (CIH-LMU) invites individuals with bachelor’s or master’s degree in health sciences or a related subject to a two days’ workshop on the 𝗦𝗲𝘅𝘂𝗮𝗹 𝗮𝗻𝗱 𝗥𝗲𝗽𝗿𝗼𝗱𝘂𝗰𝘁𝗶𝘃𝗲 𝗛𝗲𝗮𝗹𝘁𝗵 𝗥𝗲𝘀𝗲𝗮𝗿𝗰𝗵 𝗶𝗻 𝗟𝗼𝘄- 𝗮𝗻𝗱 𝗠𝗶𝗱𝗱𝗹𝗲- 𝗜𝗻𝗰𝗼𝗺𝗲 𝗖𝗼𝘂𝗻𝘁𝗿𝗶𝗲𝘀.
The workshop is organized in collaboration with Patan Academy of Health Sciences (PAHS), Nepal.
Date and time: 𝗧𝗵𝘂𝗿𝘀𝗱𝗮𝘆 𝟰𝘁𝗵 & 𝗙𝗿𝗶𝗱𝗮𝘆 𝟱𝘁𝗵 𝗼𝗳 𝗠𝗮𝘆 𝟮𝟬𝟮𝟯, 𝗳𝗿𝗼𝗺 𝟵:𝟬𝟬 𝗮𝗺 𝘁𝗼 𝟰:𝟯𝟬 𝗽𝗺, 𝗡𝗲𝗽𝗮𝗹 𝗧𝗶𝗺𝗲
𝗟𝗼𝗰𝗮𝘁𝗶𝗼𝗻: 𝗣𝗮𝘁𝗮𝗻 𝗔𝗰𝗮𝗱𝗲𝗺𝘆 𝗼𝗳 𝗛𝗲𝗮𝗹𝘁𝗵 𝗦𝗰𝗶𝗲𝗻𝗰𝗲𝘀 (𝗣𝗔𝗛𝗦), 𝗟𝗮𝗴𝗮𝗻𝗸𝗵𝗲𝗹, 𝗟𝗮𝗹𝗶𝘁𝗽𝘂𝗿, 𝗡𝗲𝗽𝗮𝗹
Mode of delivery: Face to face
𝗥𝗲𝗴𝗶𝘀𝘁𝗿𝗮𝘁𝗶𝗼𝗻 𝗱𝗲𝗮𝗱𝗹𝗶𝗻𝗲: 𝗠𝗼𝗻𝗱𝗮𝘆 𝟮𝟰𝘁𝗵 𝗼𝗳 𝗔𝗽𝗿𝗶𝗹 𝟮𝟬𝟮𝟯, 𝟭𝟭:𝟱𝟵 𝗽𝗺, 𝗡𝗲𝗽𝗮𝗹 𝗧𝗶𝗺𝗲
More information on the workshop´s content and mode of registration can be found in the attached flyer.

3 April 2023 – WHO is organizing the Fifth Global Forum on Human Resources for Health from 3 to 5 April 2023 in Geneva, Switzerland. The Forum, the largest gathering of the health workforce professionals, health policymakers and multisectoral partners is focusing on the theme of Protecting, safeguarding, and investing in the health and care workforce.
As the halfway point to the Sustainable Development Goals approaches, and three years since the COVID-19 pandemic began, population health outcomes and life expectancy are in reverse.
Health systems are dependent on health worker availability, accessibility and quality. Yet chronic shortages of health workers, underinvestment in their education and training, as well as low salaries and mismatch between education and employment strategies are leading to major challenges. The pandemic placed a heavy toll: the latest figures show that an estimated 50% of health and care workers, who already felt overworked and undervalued before COVID-19, experienced burnout from the huge additional burdens placed upon them.
“The world must take urgent action to protect and invest in health workers in all countries. Health workers need decent pay and working conditions,” said Dr Tedros Adhanom Ghebreyesus, WHO Director-General. “WHO calls for all countries to increase investment in health workforce education and jobs to meet their population needs and health system demands. This requires political leadership across all sectors, not just health”.
Marking more than five years since the adoption of the Global Strategy on Human Resources for Health: Workforce 2030, the Forum will share evidence and experiences on workforce development, as well as opportunities for a post COVID-19 era. It will examine the required policy solutions, investments, and multi-sectoral partnerships to address health and care workforce challenges and advance the implementation of the Working for Health 2022-2030 Action Plan.
WHO is recommending that all countries increase graduation of health personnel to reach 8-12% of the active workforce per annum. For instance, a country with a total of 5000 physicians would need to graduate between 400-600 physicians per annum to maintain and improve capacity in relation to population needs and health system demand.
“National responses to COVID-19 showed that the health and care workforce is capable of hugely positive change”, said Jim Campbell, Director of the Health Workforce Department. “If we want equity and universal health coverage, if we want global health security, we must protect health workers. We must invest in them, and we must take action together”.
The Forum will dedicate particular attention to health workforce investment and financing in all countries: to secure the resources for the scale-up of education and jobs. It will feature work led by the WHO African Regional Office together with Member States and regional partners in the development of the African Health Workforce Investment Charter, which aims to align and stimulate investments to halve inequities in access to health workers; especially in those African countries identified as having the greatest shortages.
The Forum is being attended by over 2000 delegates with most joining online and close to 200 participating in person. It provides a pivotal moment to focus on the topic that lies at the heart of global health agenda, taking place during the World Health Worker Week campaign, and just ahead of World Health Day, which this year marks WHO’s 75th birthday on 7 April 2023.
The outcomes of the Forum will inform the United Nations General Assembly’s High-Level Meetings on Universal Health Coverage and Pandemic Prevention, Preparedness and Response scheduled in September 2023.
WHO
World Health Day 2023: 75 years of improving public health
Overview
The World Health Organization will complete 75 years on April 7, 2023 – World Health Day. Countries joined efforts in 1948, to establish WHO to promote health, keep the world safe and serve the vulnerable – so everyone, everywhere can attain the highest level of health and well-being. On 7 April 2023, World Health Day, the World Health Organization will observe its 75th anniversary.
WHO has been working with Member States in the Region for addressing challenges, promoting Health for All, and building robust and resilient health systems. Today, the Region has eight flagship priority programmes, which are aligned to WHO’s global goals and the UN Sustainable Development Goals.
World Health Day 2023 theme: Health For All
For the public: Demand your right to access the health services you need without falling into financial hardship!
- Health For All envisions that all people have good health for a fulfilling life in a peaceful, prosperous, and sustainable world.
- The right to health is a basic human right. Everyone must have access to the health services they need when and where they need them without financial hardship.
- 30% of the global population is not able to access essential health services.
- Almost two billion people face catastrophic or impoverishing health spending, with significant inequalities affecting those in the most vulnerable settings.
- Universal health coverage (UHC) offers financial protection and access to quality essential services, lifts people out of poverty, promotes the well-being of families and communities, protects against public health crises, and moves us toward #HealthForAll.
- To make health for all a reality, we need: individuals and communities who have access to high quality health services so that they can take care of their own health and that of their families; skilled health workers providing quality, people-centred care; and policy-makers committed to investing in universal health coverage.
- Evidence shows that health systems powered by a primary health care (PHC) approach is the most effective and cost-effective way to bring services for health and well-being closer to people.
- COVID-19 set back every country’s journey to #HealthForAll.
- COVID-19 and other health emergencies, overlapping humanitarian and climate crises, economic constraints, and war, have made every country’s journey to #HealthForAll more urgent. Now is the time for leaders to take action to meet their universal health coverage commitments and for civil society to hold leaders accountable.
- Progress needs to be accelerated if health-related SDGs are to be met.
For Member States
- A blue circle with a blue plus sign in the center of it.
- Investing in strong health systems is critical for a prosperous society. Increasing public financing for health and lowering out-of-pocket health costs saves lives while advancing the Sustainable Development Goals beyond health.
- A blue circle with a blue plus sign in the center of it.
- Strong health systems are needed to deliver both universal health coverage and emergency preparedness.
- A blue circle with a blue plus sign in the center of it.
- Universal health coverage is a political and social choice. We need strong political leadership and public demand.
- A blue circle with a blue plus sign in the center of it.
- Healthy living environments can transform people’s lives.
- A blue circle with a blue plus sign in the center of it.
- WHO recommends increases in “health taxes” on tobacco, alcohol, added sugar, and fossil fuels. These taxes bring in much needed public revenues.
- A blue circle with a blue plus sign in the center of it.
- Between 2023-2030 there is a projected shortfall of 10 million health workers worldwide. Investment in education and job creation for the health sector is needed.
ACTION POINTS
- A square with a green check mark in it.
- Shift from economies driven by profit and pollution to economies driven by fairness and well-being.
- A square with a green check mark in it.
- Success must be measured by the well-being of people and healthy environments.
- A square with a green check mark in it.
- Engage and empower individuals, families and communities for increased social participation and enhanced self-care in health. Ensure informed and active participation, with people at the center of health decisions and outcomes.
- A square with a green check mark in it.
- Strengthen integrated national health systems using a PHC approach to deliver essential quality services with financial protection, with equity-oriented, gender-sensitive and rights-based programming to reach and engage those in greatest need and improve the health and well-being of all people at all ages.
- A square with a green check mark in it.
- Enable non-State actors to participate in government-led planning, progress reviews or implementation towards UHC.
- WORLD HEALTH DAY 2022: OUR PLANET, OUR HEALTH
- WORLD HEALTH DAY
- WORLD HEALTH DAY 2021: BUILDING A FAIRER, HEALTHIER WORLD FOR EVERYONE
- WORLD HEALTH DAY 2020: #SUPPORTNURSESANDMIDWIVES #COVID19
- WORLD HEALTH DAY 2019 MARKED IN NEPAL
- WORLD HEALTH DAY : HEALTH FOR ALL – EVERYONE, EVERYWHERE
- WORLD HEALTH DAY 2018 (#WORLDHEALTHDAY) MARKED
- WORLD HEALTH DAY 2018: 70TH ANNIVERSARY YEAR OF WHO
- KEY MESSAGES FOR WORLD HEALTH DAY 2018
- DEPRESSION: LET’S TALK – 7 APRIL 2017 | WORLD HEALTH DAY
- WORLD HEALTH DAY 2016: BEAT DIABETES : ACTIVITIES @ POKHARA
- WORLD HEALTH DAY 2016 : BEAT DIABETES: SCALE UP PREVENTION, STRENGTHEN CARE, AND ENHANCE SURVEILLANCE
- WORLD HEALTH DAY-2014 (SMALL BITE : BIG THREAT)
- WORLD HEALTH DAY 2015: FOOD SAFETY
- WORLD HEALTH DAY 2012 – ”AGEING AND HEALTH: GOOD HEALTH ADDS LIFE TO YEARS”
WHO certifies Azerbaijan and Tajikistan as malaria-free
A total of 42 countries or territories have reached the malaria-free milestone
29 March 2023 –– The World Health Organization (WHO) has certified Azerbaijan and Tajikistan for achieving elimination of malaria in their territories. The certification follows a sustained, century-long effort to stamp out the disease by the two countries.
“The people and governments of Azerbaijan and Tajikistan have worked long and hard to eliminate malaria,” said WHO Director-General Dr Tedros Adhanom Ghebreyesus. “Their accomplishment is further proof that, with the right resources and political commitment, eliminating malaria is possible. I hope that other countries can learn from their experience.”
Certification of malaria elimination is the official recognition by WHO of a country’s malaria-free status. The certification is granted when a country has shown – with rigorous, credible evidence – that the chain of indigenous malaria transmission by Anopheles mosquitoes has been interrupted nationwide for at least the past three consecutive years. A country must also demonstrate the capacity to prevent the re-establishment of transmission.
“Azerbaijan’s and Tajikistan’s achievement was possible thanks to sustained investment and the dedication of the health workforce, together with targeted prevention, early detection and treatment of all malaria cases. The WHO European Region is now two steps closer to becoming the first region in the world to be fully malaria-free,” said Dr Hans Henri P. Kluge, WHO Regional Director for Europe.
Azerbaijan detected its last case of locally transmitted Plasmodium vivax (P. vivax) malaria in 2012 and Tajikistan in 2014. With today’s announcement, a total of 41 countries and 1 territory have been certified as malaria-free by WHO, including 21 countries in the European Region.
Investing in universal health coverage and malaria control
Malaria control efforts in Azerbaijan and Tajikistan were strengthened through a range of investments and public health policies that enabled the governments, over time, to eliminate the disease and maintain malaria-free status.
For more than six decades, both governments have guaranteed universal primary health care. They have vigorously supported targeted malaria interventions – including, for example, prevention measures such as spraying the inside walls of homes with insecticides, promoting early detection and treatment of all cases, and maintaining the skills and capacities of all health workers engaged in malaria elimination.
Both Azerbaijan and Tajikistan utilize national electronic malaria surveillance systems that provide nearly real-time detection of cases and allow for rapid investigations to determine if an infection is local or imported. Additional interventions include biological methods of larvae control, such as mosquito-eating fish, and water management measures to reduce malaria vectors.
Since the 1920s, a sizeable portion of Tajikistan’s economy and, to a lesser extent Azerbaijan’s, has depended on agricultural production, particularly valuable cotton and rice exports.
The agricultural irrigation systems in both countries have historically also posed a malaria risk to workers. Both countries have established systems to protect agricultural workers by providing free access to malaria diagnosis and treatment in the public health care system.
Malaria control staff have the capacity to immediately test, diagnose and treat infected workers with appropriate antimalarial drugs, and to monitor and assess environmental, entomological and epidemiological risk factors. Additional programme activities include regularly assessing the judicious use of insecticides for vector control, implementing water management systems, and educating the public on malaria prevention.
WHO malaria-free certification
The final decision on awarding a malaria-free certification rests with the WHO Director-General, based on a recommendation by the independent Technical Advisory Group on Malaria Elimination and Certification. For more on WHO’s malaria-free certification process, visit this link (WHO).
- Countries in WHO South-East Asia Region renew commitment to eliminate malaria by 2030
- World Malaria Day: “Harness innovation to reduce the malaria disease burden and save lives”
- World Malaria Day
- World Malaria Report 2021: Tracking progress against Malaria
- Self-audit of the National Malaria Program using the Malaria Elimination Audit Tool
- WHO recommends groundbreaking malaria vaccine for children at risk
- National Malaria Laboratory Plan (2020-2025) and Malaria Laboratory Manual-2021
- From 30 million cases to zero: China is certified malaria-free by WHO
- Interim Guideline for Malaria Program During COVID-19 in Nepal (Updated)
- WHO launches effort to stamp out malaria in 25 more countries by 2025
- World Malaria Day 2021: Reaching the zero malaria target
- El Salvador certified as malaria-free by WHO
- WHO Guidelines for Malaria (Consolidated Guidelines for Malaria)
- Malaria Risk Areas Micro-stratification 2020
National Population and Housing Census 2021: A Report on Maternal Mortality
Overview
The Sustainable Development Goals include the target of reducing the global maternal mortality ratio (MMR) to less than 70 per 100,000 live births, with no country having an MMR that exceeds twice the global average. Nepal has committed to reduce
the MMR from 281 per 100,000 live births in 2006 to 116 by 2022, 99 by 2025, and 70 by 2030. This Nepal Maternal Mortality Study 2021 is the first ever joint undertaking of the Ministry of Health and Population (MoHP), the National Statistics Office (NSO), the Nepal Health Research Council, and health development partners for estimating the MMR and identifying the causes of maternal deaths – during pregnancy, delivery, and postpartum periods – in Nepal. By doing so, it intends to inform evidence-based policies and programs at the federal, provincial, and local levels.
Brief Methodology
The MoHP, in collaboration with the NSO, made an arrangement through a Memorandum of Understanding, where the census enumerators, as a part of their regular work, collected data on live births and deaths of women of reproductive age (WRA) in the enumerated households for the last 12 months preceding the National Population and Housing Census 2021. In the first phase, those Census enumerators then completed the death notification forms to identify pregnancy-related deaths, and submitted them to the census supervisor and notified the deaths to the pre-identified and trained local level health workers. In the second phase of the study, the local level health workers visited the household of each of the deceased women, verified the information and identified the pregnancy related deaths. For each pregnancy-related death identified, a verbal autopsy was conducted by trained health workers using the verbal autopsy form.
Major Findings
The MMR was found to be 151 per 100,000 live births in Nepal.
The MMR was found to be 151 per 100,000 live births in Nepal, with higher ratios in the Lumbini and Karnali provinces (207 and 172 per 100,000 live births respectively) and a lowest ratio in the Bagmati province (98 per 100,000 live births). Of the 12,976 deaths among women of reproductive age (15-49 years), 653 were pregnancy-related, comprising five percent of the total deaths in this age group.
- Of the 653 pregnancy-related deaths, 622 (95 percent) were classified as maternal deaths. The overall proportion of maternal deaths among the deaths of women of reproductive age was 4.8 percent. Only 611 maternal deaths were analysed further for causes and other attributes due to lack of sufficient information for 11 maternal deaths.
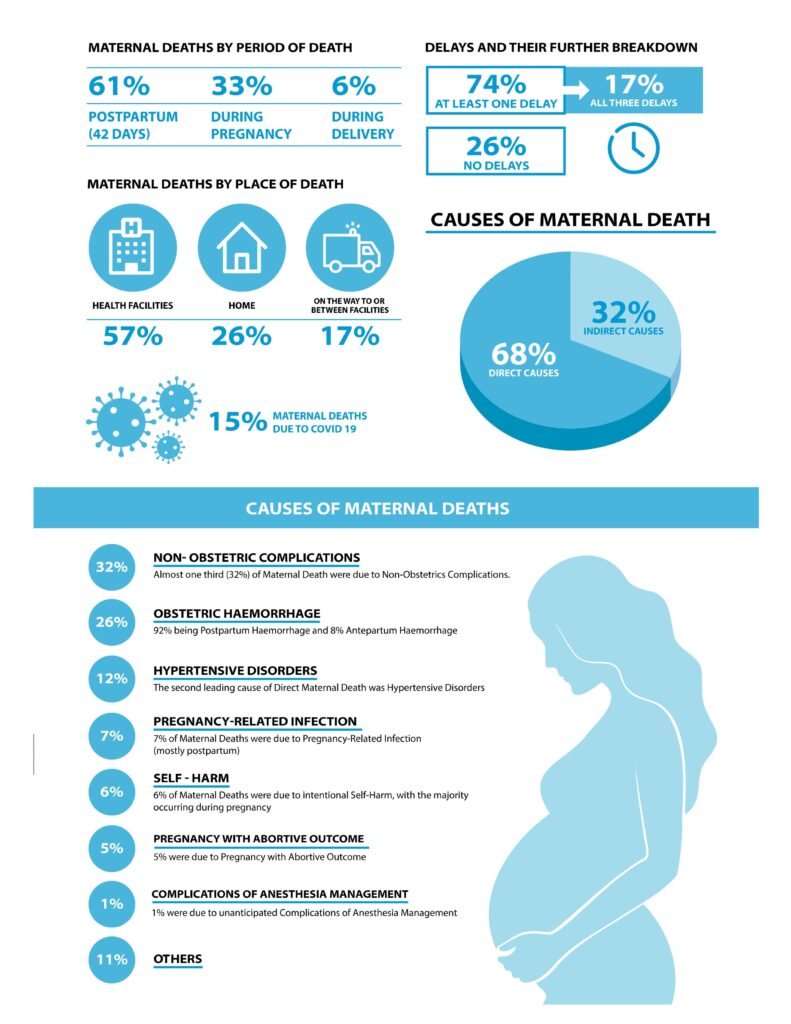
- The majority of the maternal deaths occurred in the postpartum period (61 percent), while thirty-three percent occurred during pregnancy and six percent during delivery. Nearly half of the deaths (47 percent) were reported in the Lumbini and Madhesh provinces. One in ten maternal deaths was among adolescent mothers. The majority of the deaths (57 percent) occurred in health facilities, whereas 26 percent occurred at home.
- Out of 412 women who died during delivery and postpartum period, fifty-three percent had attended all four antenatal care visits; while of the 173 women who died between 7-42 days of delivery 45 percent had attended all three postnatal care visits as per the protocol.
- Among the women who had died during delivery and in the postpartum period, over three-fourth (76 percent) had delivered at health facilities. Among those, 62 percent had delivered at government facilities while 38 percent at non- government health facility.
- Twenty-seven percent of women who died during the postpartum period had excessive bleeding, 23 percent had experienced dizziness and fainting, and 12 percent had been afflicted by fits and seizures. Eighty- three percent of the deceased had sought treatment for illness at a health facility or other place before death. Among those who did not seek treatment, nearly half did not consider it necessary (48%).
- The largest cause of maternal death was found to be non-obstetric complications (indirect maternal deaths) (32 percent). This was followed by obstetric haemorrhage (26 percent) and hypertensive disorders (12 percent). Five percent of the deaths were attributable to pregnancies with abortive outcomes. The leading causes of death during pregnancy were observed to be non-obstetric complications (40 percent), followed by direct deaths without obstetric codes (17 percent), and hypertensive disorders (14 percent). On the other hand, more than three quarters (78 percent) of deaths during delivery were attributable to obstetric haemorrhage. For deaths during the postpartum period, nearly a third were due to obstetric haemorrhage and non- obstetric complications (31 percent each).
- In connection to the “Three Delays” that lead to pregnancy-related mortality, a majority (74 percent) of the deceased women had experienced at least one type of delay, while 17 percent had experienced all three delays.
- The most common was the delay in seeking appropriate care (57 percent), followed by delay in receiving appropriate care (40 percent), and delay in reaching the healthcare facility for care (33 percent).


Conclusion
- In conclusion, the study showed that many maternal deaths in Nepal are due to preventable causes such as haemorrhage and high blood pressure during pregnancy, but a significant number are also caused by non- obstetric complications such as intentional self-harm. It highlighted the importance of improving the quality of maternal health services in health facilities and strengthening referral mechanisms, emergency transportation, and early screening for danger signs.
- In addition of its potential to strengthen community-based maternal death surveillance and response in the country, the NMMS 2021 also sets a precedent for conducting nationwide censuses of maternal deaths in future censuses to estimate the MMR and identify causes of death.
[Excerpt from Executive summary]
Download Report: National Population and Housing Census 2021: A Report on Maternal Mortality
Recommended readings
- Key Indicators: The Nepal Demographic and Health Survey (1996 NDHS- 2016 NDHS)
- The 2016 Nepal Demographic and Health Survey (2016 NDHS)
- Nepal Multiple Indicator Cluster Survey 2019 (NMICS 2019): Key findings
- Organogram and Reporting Mechanism of Nepalese Health System in Federal Context
- The 2015 Nepal Health Facility Survey: Further Analysis Reports
- Key findings – The 2015 Nepal Health Facility Survey (2015 NHFS)
- Nepal Health Facility Survey (2015 NHFS) Preliminary Report
- Health Facility Operation and Management Committee- A reference guideline for local level
- Nepal Health Facility Registry, MoHP
- Health Facility Operation Standards, 2077
- Health Facility Quality Improvement Module (QI Tool) for Health Services Strengthening