- Equity in access to health services – those who need the services should get them, not only those who can pay for them;
- that the quality of health services is good enough to improve the health of those receiving services; and
- financial-risk protection – ensuring that the cost of using care does not put people at risk of financial hardship.
Universal health coverage is defined as ensuring that all people have access to needed promotive, preventive, curative and rehabilitative health services, of sufficient quality to be effective, while also ensuring that people do not suffer financial hardship when paying for these services. Universal health coverage has therefore become a major goal for health reform in many countries and a priority objective of WHO.
Universal health coverage embodies three related objectives:
WHO
The global community has spoken: universal health coverage is right, smart and overdue. But too many people are still waiting to access quality, essential health services without financial hardship.
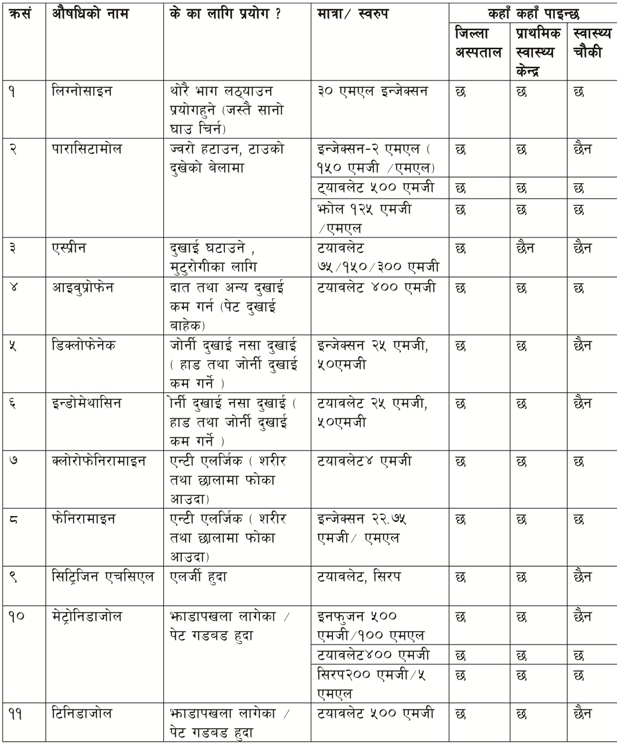
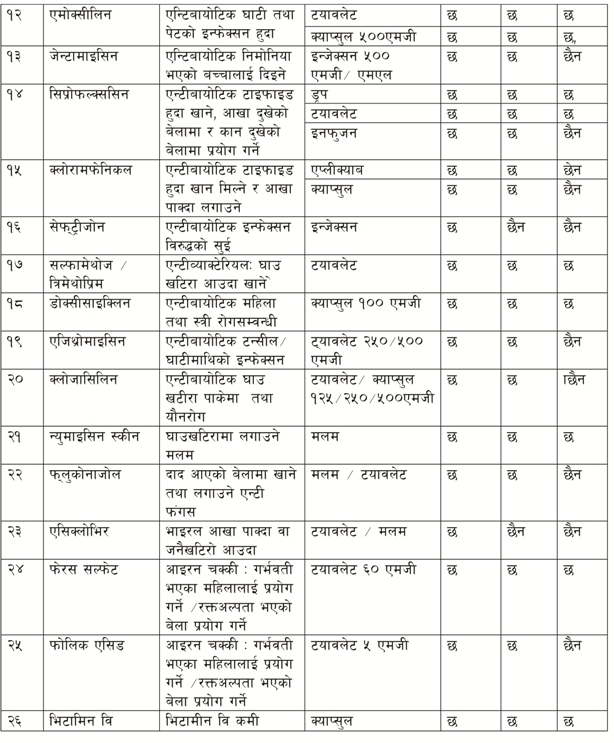
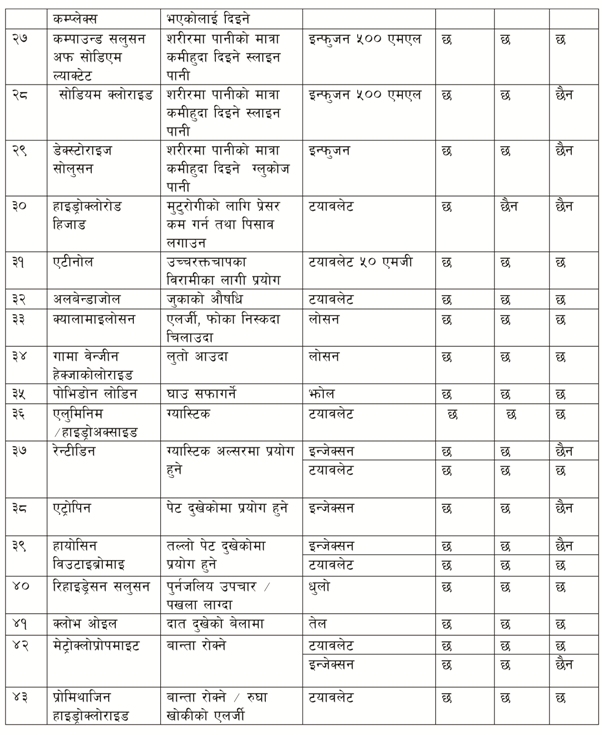
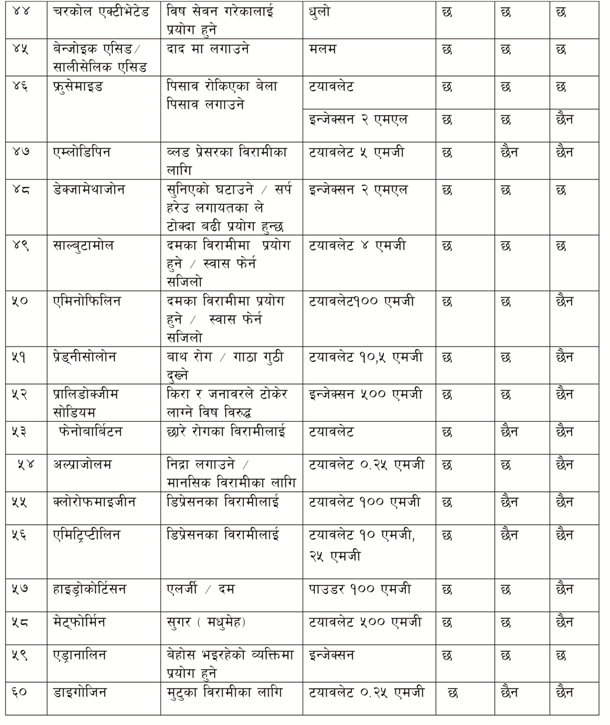
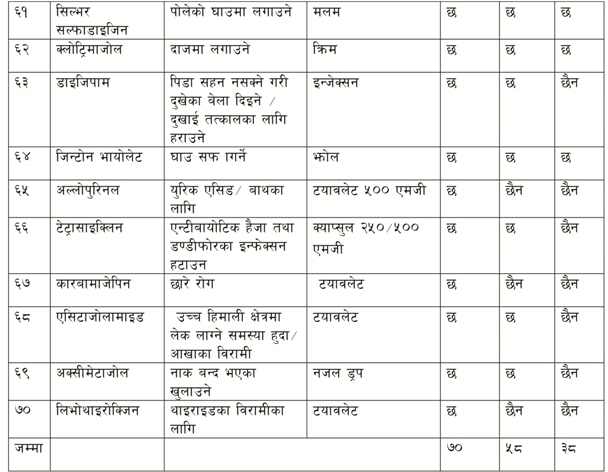
Loksewa Imp: List of Free medicines available in Nepal (Source of Info: www.nepalihealth.com)
written by Public Health Update
WHO launched a new comprehensive analysis of global health trends since 2000 and an assessment of the challenges for the next 15 years.
This report aims to describe global health in 2015, looking back 15 years at the trends and positive forces during the Millennium Development Goal (MDG) era and assessing the main challenges for the coming 15 years.
“Health in 2015: from MDGs to SDGs” identifies the key drivers of progress in health under the United Nations Millennium Development Goals (MDGs). It lays out actions that countries and the international community should prioritize to achieve the new Sustainable Development Goals (SDGs), which come into effect on 1 January 2016.
Human Rights Day is observed every year on 10 December. It commemorates the day on which, in 1948, the United Nations General Assembly adopted the Universal Declaration of Human Rights. In 1950, the Assembly passed resolution 423 (V), inviting all States and interested organizations to observe 10 December of each year as Human Rights Day.
“Our Rights. Our Freedoms. Always.”
“The right to the highest attainable standard of health” requires a set of social criteria that is conducive to the health of all people, including the availability of health services, safe working conditions, adequate housing and nutritious foods. Achieving the right to health is closely related to that of other human rights, including the right to food, housing, work, education, non-discrimination, access to information, and participation.
The right to health includes both freedoms and entitlements.
- Freedoms include the right to control one’s health and body (e.g. sexual and reproductive rights) and to be free from interference (e.g. free from torture and from non-consensual medical treatment and experimentation).
- Entitlements include the right to a system of health protection that gives everyone an equal opportunity to enjoy the highest attainable level of health.
Health policies and programmes have the ability to either promote or violate human rights, including the right to health, depending on the way they are designed or implemented. Taking steps to respect and protect human rights upholds the health sector’s responsibility to address everyone’s health.
Key facts
- The WHO Constitution enshrines “…the highest attainable standard of health as a fundamental right of every human being.”
- The right to health includes access to timely, acceptable, and affordable health care of appropriate quality.
- Yet, about 100 million people globally are pushed below the poverty line as a result of health care expenditure ever year.
- Vulnerable and marginalized groups in societies tend to bear an undue proportion of health problems.
- Universal health coverage is a means to promote the right to health.
Human rights-based approaches
A human rights-based approach to health provides strategies and solutions to address and rectify inequalities, discriminatory practices and unjust power relations, which are often at the heart of inequitable health outcomes.
The goal of a human rights-based approach is that all health policies, strategies and programmes are designed with the objective of progressively improving the enjoyment of all people to the right to health. Interventions to reach this objective adhere to rigorous principles and standards, including:
- Non-discrimination: The principle of non-discrimination seeks ‘…to guarantee that human rights are exercised without discrimination of any kind based on race, colour, sex, language, religion, political or other opinion, national or social origin, property, birth or other status such as disability, age, marital and family status, sexual orientation and gender identity, health status, place of residence, economic and social situation’1.
- Availability: A sufficient quantity of functioning public health and health care facilities, goods and services, as well as programmes.
- Accessibility: Health facilities, goods and services accessible to everyone. Accessibility has 4 overlapping dimensions:
- non-discrimination
- physical accessibility;
- economical accessibility (affordability);
- information accessibility.
5. Quality: Health facilities, goods and services must be scientifically and medically appropriate and of good quality.
6. Accountability: States and other duty-bearers are answerable for the observance of human rights. Universality: Human rights are universal and inalienable. All people everywhere in the world are entitled to them.
Policies and programmes are designed to be responsive to the needs of the population as a result of established accountability. A human rights based-approach identifies relationships in order to empower people to claim their rights and encourage policy makers and service providers to meet their obligations in creating more responsive health systems.
Fact SheetHealth in DataMaternal, Newborn and Child HealthNational Plan, Policy & GuidelinesPublic HealthPublic Health NotesPublic Health UpdateReportsResearch & Publication
2011 Nepal Demographic and Health Survey (NDHS)
written by Public Health Update
The 2011 Nepal Demographic and Health Survey (NDHS) provides up-to-date information on the population and health situation in Nepal. The 2011 NDHS is the fourth National Demographic and Health Survey conducted in the country. Repeated surveys allow for an analysis of trends over time. The survey is based on a nationally representative sample. It provides estimates at the national, ecological zone, developmental region, and in some cases, sub regional levels.
Fertility
- Total fertility rate 2.6
- Women age 15–19 who are mothers or now pregnant (%) : 17
- Median age at first marriage for women age 25–49 (years) : 17.5
- Median age at first intercourse for women age 25–49 (years) :17.7
- Median age at first birth for women age 25-49 (years) : 20.2
- Married women (age 15–49) wanting no more children (%):73
- Mean ideal number of children for women 15–49 : 2.1
Family Planning
- Current use of any modern method (currently married women 15–49) (%) : 43
- Currently married women with an unmet need for family planning (%) : 27
Maternal and Child Health
- Maternity care (women who gave birth in past 5 years) Received antenatal care from a skilled provider (%) : 58
- Births assisted by a skilled provider (%) : 36
- Births delivered in a health facility (%) : 35
- Child vaccination Children 12–23 months fully vaccinated (%) : 87
Nutrition
- Children <5 years who are stunted (moderate or severe) (%) : 41
- Children <5 years who are wasted (moderate/evere) (%): 11
- Children <5 years who are underweight (moderate/severe) (%) : 29
- Median duration of any breastfeeding (months) : 33.6
- Median duration of exclusive breastfeeding (months) 4.2 3
- Prevalence of anemia in children 6-59 months (%) : 46
- Prevalence of anemia in women age 15-49 (%) : 35
Childhood Mortality (Number of deaths per 1,000 births)
- Infant mortality (between birth and first birthday) : 46
- Under–five mortality (between birth and fifth birthday) : 54
Health SystemsMaternal, Newborn and Child HealthNational Plan, Policy & GuidelinesPublic HealthPublic Health NotesPublic Health ProgramsResearch & Publication
National Female Community Health Volunteers (FCHVs) Program
written by Public Health Update
Background
Recognizing the importance of women’s participation in promoting health of the people, GoN initiated the Female Community Health Volunteer (FCHV) Program in FY 2045/46 (1988/1989) in 27 districts and expanded to all 75 districts of the country in a phased manner.
Initially, the approach was to select one FCHV per ward regardless of the population size. Later in 2050 (1993/94) population based approach was introduced in selected (28) districts. All together there are 51,470 FCHVs in the country (47,328 FCHVs at rural/VDC level and 4,142 at urban/municipality level). FCHVs are selected by members of Mothers’ Group for Health (MG‐H) with the help of local health facility staff.
They are provided 18 days basic training in two phases (9+9 days) on selected primary health care components. After completion of basic training, FCHVs are provided with a certificate and medicine kit box consisting of necessary drugs and supplies free of cost.
They are also provided with manuals, flip chart, ward register, IEC materials, FCHV bag, signboard and identity card. Family Planning devices (pills and condoms only to FCHVs) are supplied regularly through local health facility.
The major role of the FCHV is to promote health and healthy behaviors of mothers and community people to promote safe motherhood, child health, family planning, and other community based health services. FCHVs distribute condoms and pills, ORS packets and vitamin A capsules, treat pneumonia cases and refer more complicated cases to health institution along with motivation and education to community people. Similarly, they also distribute iron tablets to pregnant women.
Various policies, strategies and guidelines have been developed to strengthen the FCHV program. Numerous factors influence the program including national health sector reform, decentralization and handing over of health facilities to VDCs, experience gained from program implementation, and the recognition to FCHVs in reduction of maternal and child mortality and general fertility through continuous implementation of community‐based health programs in Nepal.
The FCHV program strategy has been revised in 2067 (2010) which gave strategic directions and critical approaches to ensure a strengthened national program for consistency and continuous support to each FCHV. Government of Nepal is committed to increase the moral & participation of FCHV in community health development. In fiscal year 2064/65 MoHP established FCHVs fund by providing cash support of Rs. 50,000 to each VDC. The mobilization of this fund for income generation activities is expected to benefit the FCHVs and the community at large.
Goal
The goal of FCHV program is to support national goal of health through involvement of community in public health activities. This includes imparting knowledge and skills for empowerment of women, increasing awareness on health related issues and involvement of local institutions in promoting health care.
Objective
FCHV program has the following objectives:
- To prepare a pool of self‐motivated volunteers as a focal person to bridge health programs with community
- To prepare a pool of volunteers to provide community based health services
- To activate women to tackle common health problems by imparting relevant knowledge and skills
- To increase the community participation in improving health
- To develop FCHV as a motivator for health
- To increase utilization of health care services through demand creation
Summary
The major role of the Female Community Health Volunteers (FCHVs) is promotion of safe motherhood, child health, family planning, and other community based health services to promote health and healthy behavior o
f mothers and community people with support from health workers and health facilities. At present there are 51,470 FCHVs (47,328 FCHVs at rural/VDC level and 4,142 at urban/municipality level) actively working all over the country. FCHVs contributed significantly in the distribution of oral contraceptive Pills, Condoms and Oral Rehydration Solution (ORS) packets and counseling and referring to mothers in the health facilities for the service utilization. FCHVs have contributed in distribution of 53 percent oral pills and 47 percent ORS packets at the national level. FCHVs distributed a total of 14,506,525 packets of condoms in the FY 2070/71. Service statistics shows that more than one half of the diarrhoea and ARI cases were treated by FCHVs.

The International Volunteer Day (IVD) mandated by the UN General Assembly, is held each year on 5 December. It is viewed as a unique chance for volunteers and organizations to celebrate their efforts, to share their values, and to promote their work among their communities, non-governmental organizations (NGOs), United Nations agencies, government authorities and the private sector.
The theme of International Volunteer Day 2015 is ”The world is changing. Are you? Volunteer!”
IVD 2015 is challenging every one of us to be part of implementing the newly launched Global Goals, the 2030 Agenda for Sustainable Development.
United Nations
![]() |
| Add caption |
Similarly, The 12th Female Community Health Volunteers’ Day is celebrated across the country on Saturday by organizing various activities in districts, and in community level health institutions across the country.
The slogan for National FCHVs Day is
”mahila swaasthya sewika ko sewa
swasthya samaaj ko laagi TEWAA’‘
![]() |
| FCHVs Lekhnath 14 and 15 |
The Female Community Health Volunteer (FCHV) Programme IN Nepal was started in 1988 by the Ministry of Health and Population in order to improve community participation and to enhance the outreach of health services through local women working voluntarily. Initially the strategy proposed one FCHV per ward in rural areas.
In the mid-1990s a “population based” strategy was adopted in 28 districts whereby additional FCHVs were recruited leading to a current total of nearly 50,000 FCHVs in Nepal and 97 % of them are in are in the rural areas.
FCHVs play an important role in contributing to a variety of key public health programs, including family planning, maternal care, child health, vitamin A supplementation/ de-worming and immunization coverage. They are the foundation of Nepal’s community-based primary health care system and are the key referral link between the health services and communities. Additionally FCHVs have made significant contributions to women’s leadership and empowerment at the Village Development Committee (VDC) level, and several active FCHVs are as VDC members.
Key facts
(Source of Info: World Health Organization)
Fact sheet N°360
Updated November 2015
- HIV continues to be a major global public health issue, having claimed more than 34 million lives so far. In 2014, 1.2 [980 000–1.6 million] million people died from HIV-related causes globally.
- There were approximately 36.9 [34.3–41.4] million people living with HIV at the end of 2014 with 2.0 [1.9–2.2] million people becoming newly infected with HIV in 2014 globally.
- Sub-Saharan Africa is the most affected region, with 25.8 [24.0–28.7] million people living with HIV in 2014. Also sub-Saharan Africa accounts for almost 70% of the global total of new HIV infections.
- HIV infection is often diagnosed through rapid diagnostic tests (RDTs), which detect the presence or absence of HIV antibodies. Most often these tests provide same day test results; essential for same day diagnosis and early treatment and care.
- There is no cure for HIV infection. However, effective antiretroviral (ARV) drugs can control the virus and help prevent transmission so that people with HIV, and those at substantial risk, can enjoy healthy and productive lives.
- It is estimated that currently only 53% of people with HIV know their status. In 2014, approximately 150 million children and adults in 129 low- and middle-income countries received HIV testing services.
- By mid-2015, 15.8 million people living with HIV were receiving antiretroviral therapy (ART) globally.
- Between 2000 and 2015, new HIV infections have fallen by 35%, AIDS-related deaths have fallen by 24% with some 7.8 million lives saved as a result of international efforts that led the global achievement of the HIV targets of the Millennium Development Goals.
- Expanding ART to all people living with HIV and expanding prevention choices can help avert 21 million AIDS-related deaths and 28 million new infections by 2030.
Global Health Issues
25 November 2015
International Day for the Elimination of Violence against Women
WHO releases a new tool for medical and legal professionals to ensure that proper evidence is collected in cases of sexual violence to help bring justice for victims. The goal is to end impunity for perpetrators of sexual violence and help eliminate violence against women. Globally 1 in 3 women has been a victim of physical/sexual partner violence in her lifetime.
Although anyone can be a victim of violence, including children and women and men of all ages, recent global figures indicate that one in three women globally have experienced physical and/or sexual violence by an intimate partner or sexual violence by someone other than a partner in their lifetime. Women who experience partner violence are twice as likely to suffer from depression and 1.5 times more likely to have a sexually transmitted infection including HIV, compared to those who have never been exposed to such violence. They are also more likely to have unwanted pregnancies, unsafe abortions and when the violence occurs during pregnancy to suffer miscarriages, stillbirths, premature births and to have low birth weight babies. Situations of conflict, post conflict and displacement may exacerbate existing forms of violence and present additional forms of violence against women. WHO works to address violence against women by helping strengthen the role of the health sector within a multi-sectoral approach to prevention and response.Download:
This toolkit is practitioner focused and provides practical guidance to help support service provision and coordination of the medico-legal response in low-resource settings. It contains one-page reference cards on, for example, conducting a forensic examination, taking a statement, ethical issues, to enable quick and easy access to basic and key information. It is part of a World Health Organization and United Nations Office on Drugs and Crime (UNODC) project on Strengthening Medico-Legal Services for Sexual Violence Cases in Conflict-Affected Settings, supported by United Nations Action against Sexual Violence in Conflict (UN Action).